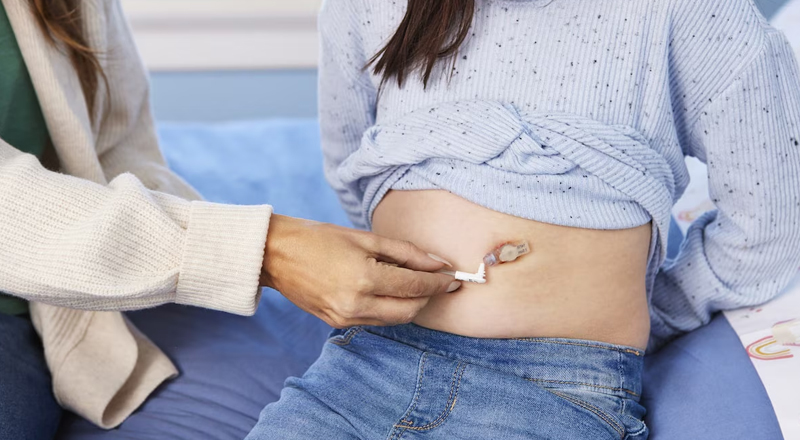
Feeding Tube Support (PEG/RIG)
Maintaining adequate nutrition is essential throughout head and neck cancer treatment. Surgery, radiotherapy, and chemotherapy can significantly affect a patient's ability to eat and swallow, leading to weight loss, malnutrition, and treatment interruption. Enteral feeding via a gastrostomy tube — placed as a Percutaneous Endoscopic Gastrostomy (PEG) or Radiologically Inserted Gastrostomy (RIG) — provides nutritional support when oral intake is insufficient. Dr. Antony Raj James considers nutritional support planning as an integral component of head and neck cancer care.
What is a Gastrostomy Tube?
A gastrostomy tube is a feeding tube inserted through the abdominal wall directly into the stomach, allowing liquid nutrition, fluids, and medications to be delivered without the need to swallow. It bypasses the mouth and throat entirely, making it suitable when swallowing is unsafe, severely impaired, or temporarily not possible during treatment.
PEG vs. RIG — What is the Difference?
- Percutaneous Endoscopic Gastrostomy (PEG) – Inserted using an endoscope (flexible camera) passed through the mouth and down into the stomach, combined with an external abdominal puncture. Performed under sedation. It is the most common method when upper aerodigestive tract endoscopy is feasible.
- Radiologically Inserted Gastrostomy (RIG) – Inserted under radiological (X-ray or fluoroscopy) guidance through the abdominal wall, without endoscopy. Preferred when endoscopic access is difficult due to tumor obstruction, severe trismus, or other anatomical constraints common in head and neck cancer patients.
When is a Feeding Tube Recommended in Head & Neck Cancer?
A gastrostomy tube may be recommended in the following situations:
- Pre-operatively, when significant post-operative swallowing impairment is anticipated following major surgery (prophylactic gastrostomy)
- During or after radiotherapy to the head and neck, when treatment-related mucositis and dysphagia prevent adequate oral intake
- When aspiration risk makes oral feeding unsafe
- When patients are significantly malnourished at presentation and require nutritional optimisation before treatment
- During chemoradiotherapy for locally advanced head and neck cancers
Prophylactic vs. Reactive Gastrostomy
The decision to place a feeding tube prophylactically (before treatment-related swallowing difficulties arise) versus reactively (when a patient is already struggling to eat) depends on individual patient and tumor factors. Pre-treatment placement avoids an urgent procedure during active treatment and reduces the risk of aspiration and weight loss. However, prophylactic feeding tubes may potentially affect swallowing rehabilitation if not accompanied by continued oral intake and therapy where possible. The decision is individualized through multidisciplinary discussion.
Tube Removal and Transition to Oral Feeding
Gastrostomy tubes are removed once a patient has demonstrated safe and adequate oral intake following swallowing rehabilitation assessment. The goal of the care pathway is to support nutrition during treatment and rehabilitation while working towards restoration of independent oral feeding wherever possible.
Why Choose Dr. Antony Raj James?
- Specialized Head & Neck Oncology Training – MCh in Head & Neck Oncology from Tata Memorial Hospital/ACTREC, Mumbai.
- Integrated Nutritional Planning – Feeding tube need assessed and planned as part of the overall cancer treatment pathway.
- Multidisciplinary Coordination – Gastrostomy planning involves dietitians, speech-language therapists, radiation oncologists, and the nursing team.
- Patient-Centred Approach – Nutritional support tailored to treatment phase, functional status, and rehabilitation goals.